Pain is usually the initial signal a person gives you, and occasionally the only one you get in a noisy emergency situation bay. Handling it well is not concerning distributing analgesia on a timetable. It is judgement moving: reviewing the person, determining risk, collaborating with the team, and providing the appropriate intervention at the correct time. That is the core of PUAEME008 Offer Pain Administration, the system that underpins secure, effective prehospital and acute treatment analgesia across Australia. For nurses who intend to develop their method in high‑stakes setups, understanding this device is both an expert edge and a patient safety and security imperative.
This overview unboxes what PUAEME008 actually resembles in technique, why it matters for registered nurses, and how to convert training right into positive, ethical care. It draws on real-world instances, common mistakes, and the subtleties that sit behind cool flowcharts.
What PUAEME008 covers, in practice
The title sounds straightforward: supply discomfort monitoring. The information is not. The system concentrates on fast, systematic pain evaluation; safe selection and administration of analgesics within extent; keeping an eye on for negative effects; and rise when red flags arise. It likewise emphasises approval, documents, and teamwork.
In concrete terms, that indicates you should be able to take an individual from first get in touch with to safe handover while controlling discomfort and not creating harm. You recognise when medicinal options pain management certification are proper, when non-pharmacological steps will add worth, and when to pause and reassess because the medical diagnosis is unstable. You operate within local methods and your credentialed scope, which could include inhaled methoxyflurane, intranasal fentanyl, IV morphine, or ketamine, depending on your organisation.
PUAEME008 sits conveniently together with discomfort management training for registered nurses delivered via brief programs in pain management or a broader pain administration certificate training course. Many carriers map their pain management training programs to this system to assist learners gain a country wide recognised statement of accomplishment, or pile the unit into a certificate program in pain management that includes wider modules in evaluation, pharmacology, and communication.
Why nurses take advantage of aligning with PUAEME008
You already evaluate pain every change. The worth of an organized unit is consistency under pressure. In an emergency division, rescue affair, remote facility, or access team, consistency suggests less misses out on and safer decisions. Registered nurses that finish a pain monitoring qualification or a targeted discomfort management course straightened to PUAEME008 often tend to relocate much faster from acknowledgment to intervention. They additionally record much more plainly, an essential Article source protect when handovers span several teams and hours.
For managers, registered nurses credentialed in puaeme008 give pain monitoring bring measurable renovations. Less accelerations for preventable oversedation. Much better patient complete satisfaction ratings. Much shorter time-to-analgesia, which reduces anxiety and secondary injuries from unchecked pain.
There is a personal measurement as well: self-confidence. Few things transform the tone of a shift like understanding you can de-escalate serious discomfort securely while the medical group types the underlying cause.
The anatomy of reliable pain assessment
Numbers aid, but they are not the whole story. You need to triangulate 3 streams of information: person record, evident behaviour, and physiological context.
Start with the client's words. A numerical score range supports the discussion, yet it can misinform. A stoic farmer with a substance shin might report five out of 10 because he intends to avoid opiates. An anxious teenager with renal colic might report ten out of 10 and hyperventilate. Take the number, after that ask what the pain feels like, where it began, whether it radiates, and what aggravates or alleviates it. Quality guides your differential; sharp pleuritic discomfort and dull stress are different beasts.
Watch the body. Guarding, splinting, light clammy skin, shaking, or flinching at light touch all tell you how the nerves is responding. People with cognitive problems, mental deterioration, or language obstacles require extra treatment. In these instances, discomfort evaluation tools designed for nonverbal clients make their keep, but you still need to review the space: household input, behavioral adjustments from standard, and the professional context.
Layer in physiology. A heart price up 20 beats from baseline, blood pressure modifications, and respiratory pattern shifts can indicate both discomfort and decompensation. In a trauma individual with borderline perfusion, selections concerning analgesia step from straightforward comfort to hemodynamic strategy.
This comprehensive method is embedded in strong discomfort monitoring training, and it is the factor numerous pain administration courses for nurses invest as much time on evaluation as on pharmacology.
Medication options within range and context
PUAEME008 acknowledges variant in neighborhood authorisations. Some solutions support inhaled methoxyflurane for moderate to serious injury discomfort, intranasal fentanyl for rapid, needle‑free relief, or IV morphine in monitored setups. Others include ketamine for serious discomfort, especially when hypotension is a concern.
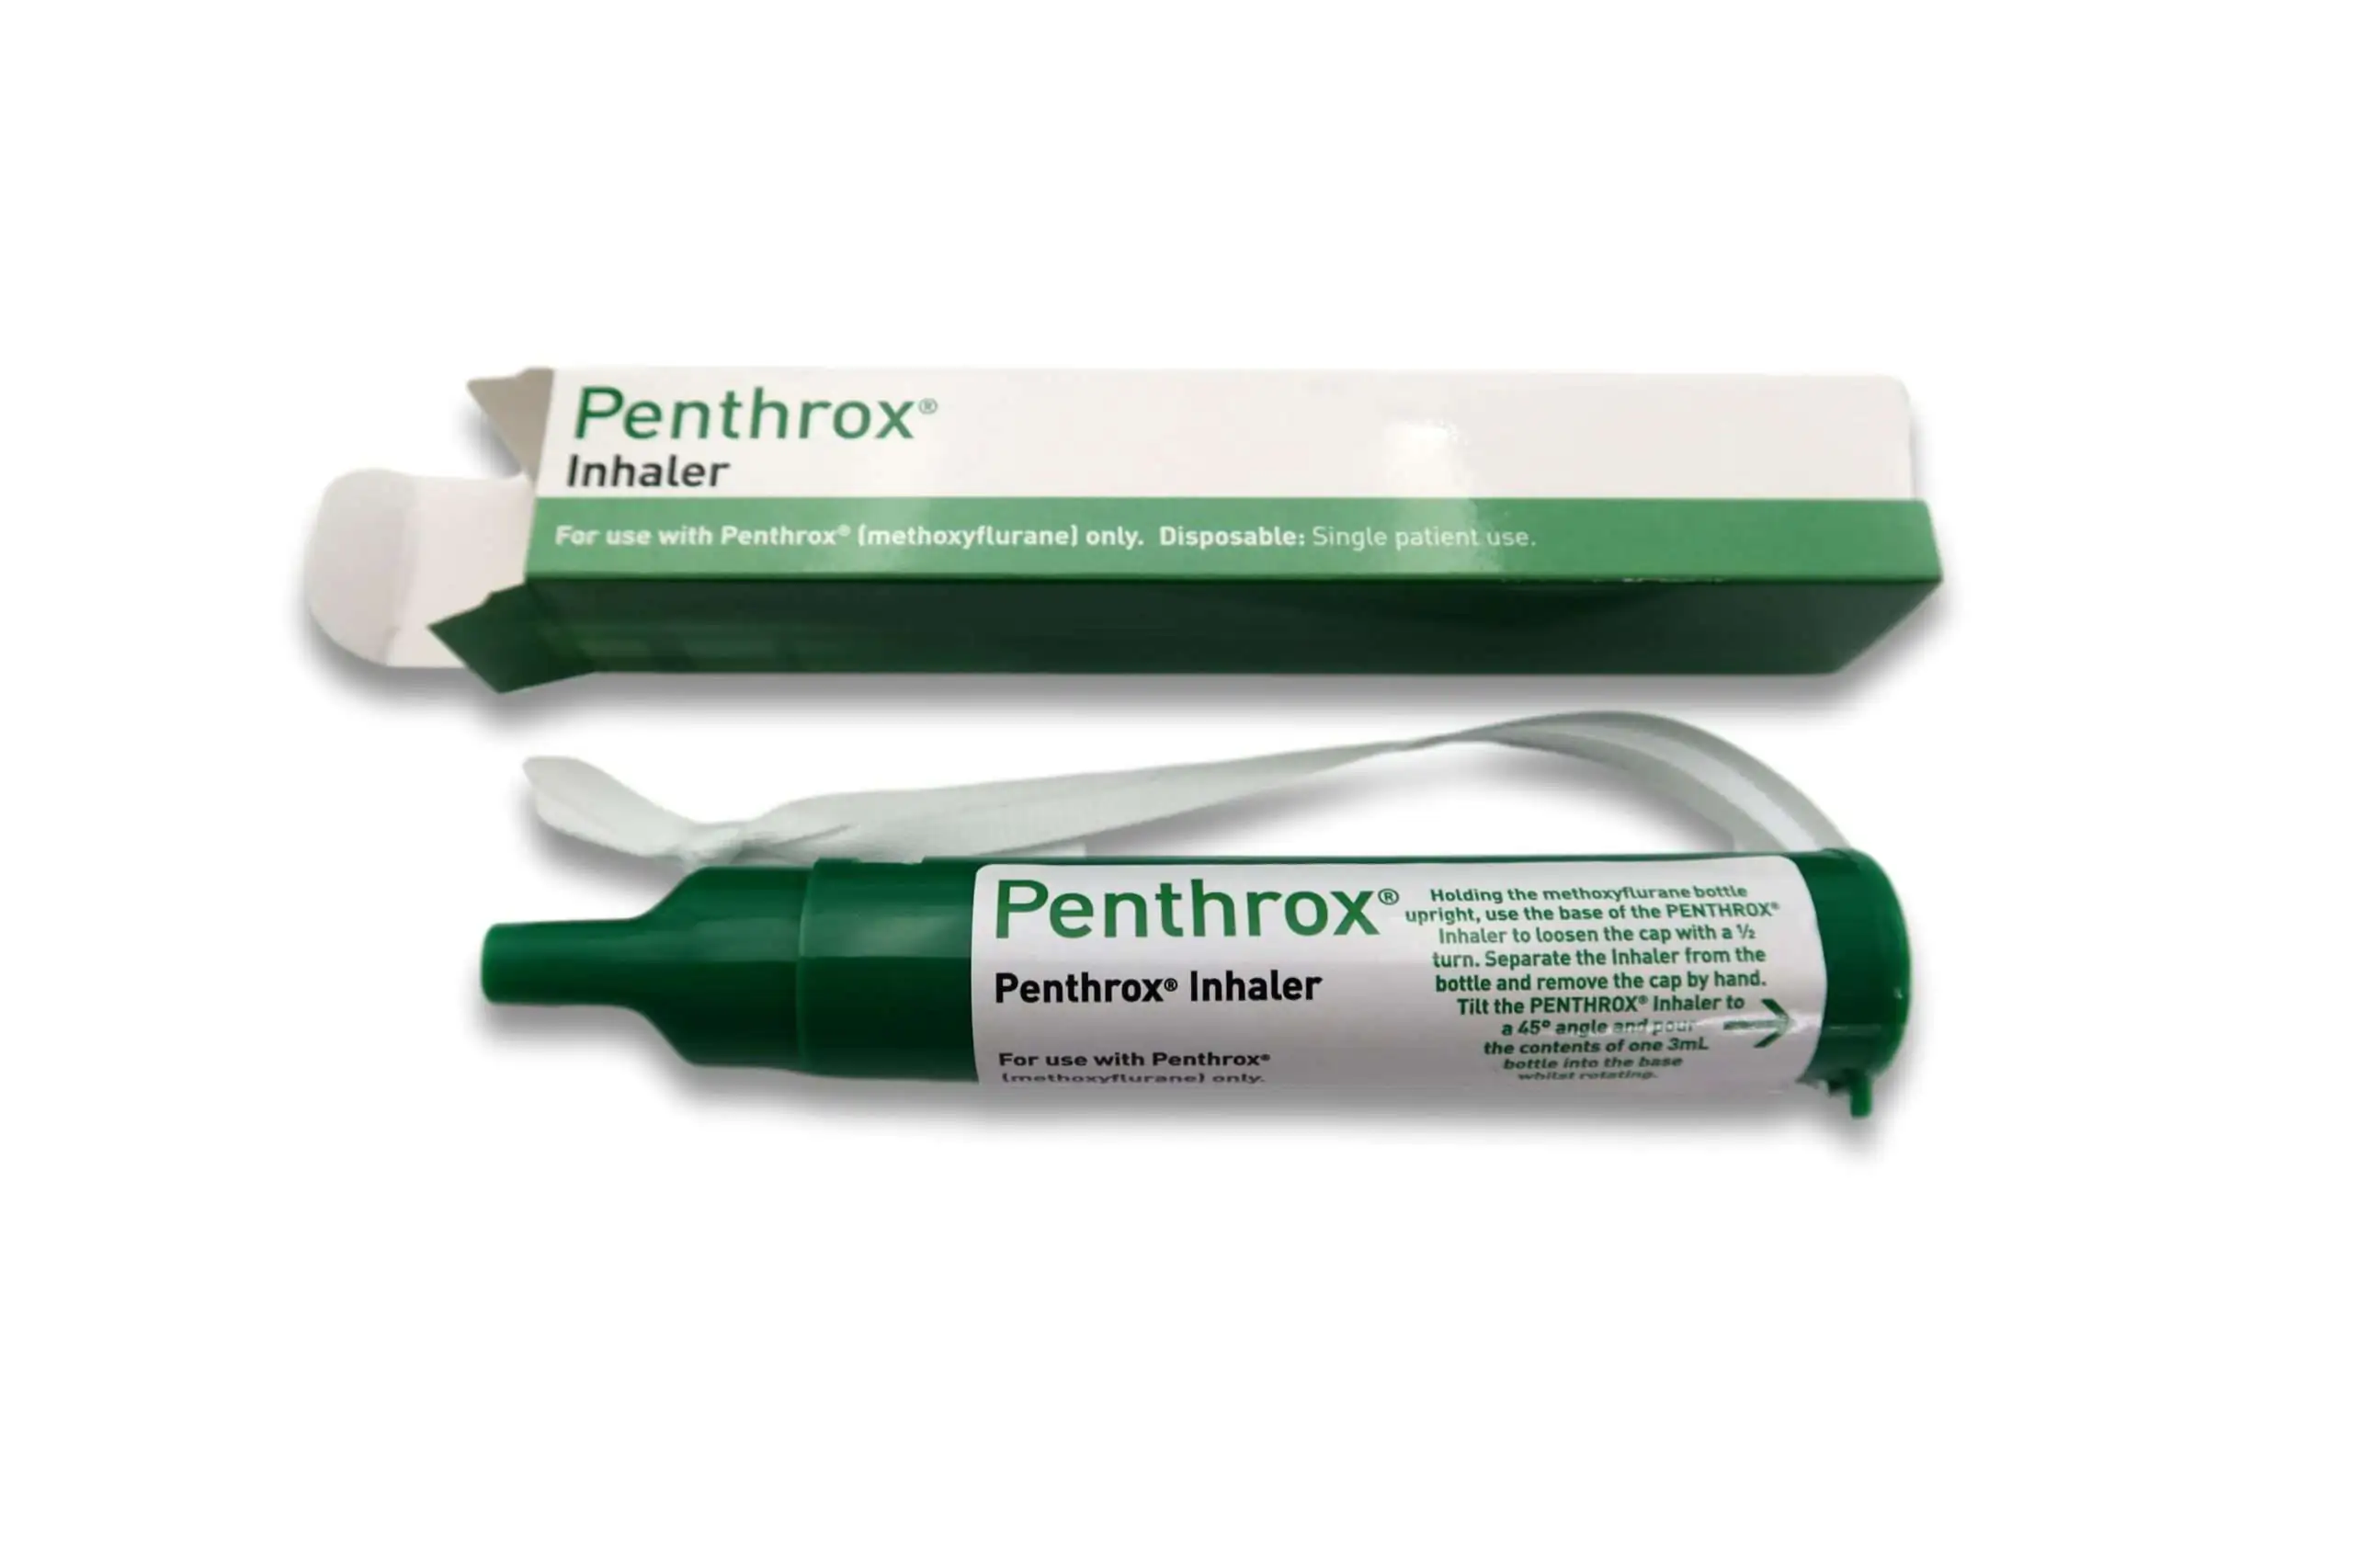
Methoxyflurane is forgiving on the hemodynamics and simple to administer. It can bridge the space while you protect IV gain access to or established a block. Side effects generally include lightheadedness and nausea or vomiting. It is unsuitable in significant kidney problems or in clients with malignant hyperthermia threat. I have seen it save an otherwise uncontrollable extrication, the individual mentoring themselves with the whistle in between breaths while we splinted and moved.
Intranasal fentanyl offers speed when time and veins are limited. Quick onset, brief period, and foreseeable titration in tiny aliquots. The risk is breathing anxiety, more than likely in the sickly, the intoxicated, or when mixed with sedatives. Monitoring is non-negotiable: respiratory system price, oxygen saturation, mental standing. If you operate in a service that uses it, have naloxone ready and a mental version of turnaround dosing.
IV morphine continues to be a staple, specifically for cracks, burns, and postoperative discomfort. Titrate gradually, reassess after each little dosage, and regard the lag in between administration and peak effect. The most usual error I see in brand-new professionals is impatience in the first five minutes adhered to by overshoot. Clock time and patient time do not match when the area is busy.
Ketamine is invaluable when you require analgesia without going down blood pressure. At analgesic dosing, dissociation is unusual, yet anticipate strange understandings. Alert the patient about a "floaty" sensation. Co-administer a little benzodiazepine just if your local protocol supports it and the client's breathing book is strong. In injury, ketamine can unlock splinting and alignment that would or else be unbearable.
Non-opioid accessories have a place. Paracetamol for standard control, NSAIDs when hemorrhaging danger is low, regional anaesthetic infiltration or regional blocks if you are educated and authorised. A well-placed femoral nerve block can transform an experience right into a workable transfer and reduce overall opioid load.
Non-pharmacological measures are not decoration
Talk is a method. A calmness, specific description reduces fear, and are afraid magnifies pain. Immobilisation, altitude, ice, warmth, and gentle positioning are fundamental yet effective. Interruption functions throughout ages. For burns, amazing running water very early and non-adherent dressings later supply discomfort relief that medicines can not match. In a delirious person, dim light and a familiar voice may do more than one more milligram of opioid.
Most discomfort administration training courses ignore exactly how to sequence these choices. The order matters. Immobilise initially in arm or leg injuries, after that consider breathed in or intranasal representatives. Air conditioning before analgesia is sensible in small burns, but in extensive burns go for analgesia during clothing to avoid hypothermia and distress.
Red flags that bypass routine
Some discomfort need to not be blunted until you ensure the medical diagnosis. Undifferentiated abdominal pain in an unstable patient warrants slim, mindful titration if any kind of. Analgesia does not odd peritonitis, however excessive sedation can postpone important indicators like protecting or modified mental condition. Abrupt severe frustration "worst ever before" with neurological adjustment requires neurology and imaging. Pain in the back with saddle anesthetic or brand-new weakness is a medical clock. In these circumstances, PUAEME008 does not advise you to keep convenience. It asks you to balance alleviation with diagnostic stewardship and to escalate quickly.
For upper body pain, analgesia can aid, yet opioids may drop high blood pressure and mask ongoing ischemia signs. Antiplatelets, nitrates if indicated, and oxygen just if hypoxic are the essentials. Treat discomfort while you function the method, not instead of it.

The art of titration and the technique of monitoring
Good pain management is seldom a solitary large dose. It is a collection of little, gauged steps, each followed by review. The review is the component that tends to slide when the phone rings and the bed alarm system goes off. Build a micro-routine: dose, two minutes observing respiratory system rate and speech, inspect the patient's description, file. If you can not see, you can not dose. Delegate or delay.
Monitoring ought to match the risk. For inhaled methoxyflurane, observe level of consciousness, wooziness, and nausea or vomiting. For opioids, include breathing price, oxygen saturation, and capnography if available. For ketamine, screen high blood pressure and emergence reactions. Pain ratings aid track impact, yet prevent chasing after a number to no. Practical objectives matter much more: can the client take a full breath, remainder in between convulsions, allow safe repositioning.
Consent, capability, and culture
Consent in emergency situation discomfort administration is often implied, but not constantly. An aware, focused individual that refuses an opioid due to previous dependency is exercising autonomy. Offer options, discuss your thinking, and respect the decision. If the patient does not have capability due to head injury or shock, act in their best interests using the very least limiting methods and record your rationale.
Cultural considerations shape exactly how individuals share discomfort and approve therapy. In some neighborhoods, stoicism is a merit, in others, vocal expression is expected. Do not correspond volume with extent or peaceful with convenience. Usage interpreters whenever language obstacles exist, and prevent leaning on household to convert medical nuances like threats of sedation.
Documentation that shields patients and practitioners
Good notes are not verbose, they are structured. Catch the first assessment with descriptors, not simply a number. Record what you provided, dosage, time, route, and action. If you differed normal application as a result of comorbidities or accessibility issues, state so. Include unfavorable effects and the activities taken. If you are working within a pain administration qualification program structure, your assessors will certainly look for this logic trail. In reality, future you will certainly be happy when the specialist asks what happened before transfer.
What proficient efficiency looks like across settings
Consider a country nurse confronted with a rollover and a 60‑year‑old with an undoubtedly fractured humerus, hypotensive however chatting. The registered nurse applies a sling and swathe to immobilise, carries out methoxyflurane while preparing an IV line, and demands retrieval. High blood pressure stabilises with fluids and pain control. Intranasal fentanyl adheres to in small doses to keep comfort during the long wait, with crucial signs kept an eye on and recorded every five minutes. The nurse explains the feelings anticipated from methoxyflurane, checks for renal issues, and validates no personal or household history of deadly hyperthermia. On handover, the access group praises the titration and the clear notes. That is PUAEME008 in action.
In a metropolitan ED, a client with a displaced ankle fracture shows up in serious pain. The triage registered nurse starts analgesia within the quick analysis zone: intranasal fentanyl titrated to useful relief so that radiography is possible, followed by a regional block by a credentialed clinician. The registered nurse prepares for nausea, has an emesis bag all set, and provides easy descriptions to keep relationship. The client stays clear of throwing up, keeps oxygen saturation stable, and undertakes a smooth decrease. Minutes shaved, distress reduced.
Common mistakes and how to prevent them
Over-reliance on single methods results in aggravation. If all you have is IV morphine, you may under-treat since gain access to is postponed or the client is needle-phobic. Build a layered plan that transitions from breathed in or intranasal agents to IV as proper. One more trap is application by practice rather than weight, age, and comorbidity. Frail older adults require smaller increments and longer stops between dosages. People with rest apnea or persistent obstructive pulmonary illness are sensitive to respiratory depression; maintain the head raised, think about lower opioid dosages, and use capnography when you can.
A 3rd challenge is ignoring non-pharmacological care while going after a number. A well-padded splint or mild repositioning can halve an analgesic demand. Lastly, teams in some cases fail to remember to discuss what the individual will certainly really feel. When a patient recognizes methoxyflurane can create faintness, they will not stress. When ketamine's perceptual changes are anticipated in ordinary language, you reduce fear.
Training paths that map to PUAEME008
For nurses, the best entry is a program plainly lined up to PUAEME008 Provide Pain Monitoring, with sensible assessment under supervision. Seek training courses that include online circumstances, not just e-learning. Top quality pain administration training for registered nurses mixes short theory components with hands-on practice using methoxyflurane tools, intranasal atomisers, and IV cannulation where within scope.
If you need credentials quickly, brief programs hurting management can solidify skills without lengthy research study obstructs. For wider scope or leadership functions, a pain monitoring qualification program that sets PUAEME008 with advanced assessment, opioid stewardship, and regional methods is worth the moment. Numerous organisations will approve a pain management certificate as part of your credentialing documents, especially if the supplier is recognised and the evaluation consists of direct monitoring. If you are working together with allied health, take into consideration cross-disciplinary sessions. Pain management programs for physiotherapists often excel in non-pharmacological techniques that registered nurses can incorporate right into intense treatment plans.
Clinicians in prehospital or urgent treatment settings ought to verify that their selected program teaches emergency situation pain management in sensible contexts. Request data on teacher experience, circumstance hours, and post-course assistance. Some providers consist of a refresher library for six to twelve months, which assists with ability retention.
Skill maintenance and audit
Skills discolor without repetition. Set up refresher courses every 6 to one year for high-risk medicines. Run short simulations during group gathers: one five-minute go through of intranasal dosing and surveillance buys a lot of security. Keep a basic audit: time-to-analgesia from triage or very first contact, portion of people with recorded reassessment within 10 mins, and incidents of adverse events. When numbers wander, target training. If your service utilizes a provide discomfort management course aligned with PUAEME008, develop its competencies right into your annual appraisal.
Ethical technique in the age of opioid stewardship
Safe analgesia should live along with a fact: opioids can damage. Stewardship does not suggest keeping required relief, it indicates precision. Use the lowest effective dosage, pair with non-opioid techniques where feasible, and plan for de-escalation. For recognized persistent pain patients, stay clear of replicating their baseline opioids while you address intense exacerbations. Verify present programs, take into consideration resistance, and work together with discomfort solutions when offered. Provide take-home instructions that expect rebound discomfort and nausea or vomiting, and make sure clients recognize that to call if symptoms escalate.
Communication as scientific intervention
Words carry as much weight as milligrams. When you walk in tranquil, name the likely source of discomfort in ordinary language, and detail what you will do, high blood pressure usually goes down a couple of factors before any medication goes into. Invite inquiries. Show what you see: "Your breathing is easing with this dose. We will certainly give one more small amount and keep enjoying your oxygen." This running commentary builds trust fund and helps you discover modifications. Households cool down, which releases your hands and focus for the patient.
Building a regional method that works
Even the best educated registered nurse struggles without a clear procedure. If you have influence in your device, form a concise formula that fits your formulary and equipment. Maintain it on one web page at the bedside: evaluation hints, first-line options by intensity, titration steps, keeping track of requirements, and specific cautions. Consist of a short area on patients with minimal capability or language barriers. Make it simple to follow under stress. Straighten it clearly to PUAEME008 to sustain training, compliance, and audit.
A short, practical checklist for the next shift
- Verify scope, stock, and tools for analgesia at the start of shift; check methoxyflurane products, intranasal atomisers, and turnaround agents. Assess discomfort utilizing words, practices, and physiology; record descriptors, not just a number. Choose the aligned technique for the circumstance; titrate in little actions and reassess after each dose. Layer non-pharmacological actions early; immobilise, placement, and connect clearly. Monitor and paper feedback and damaging results; intensify when red flags or atypical patterns appear.
The throughline: proficiency as habit, not heroics
Mastering PUAEME008 is much less regarding memorizing medicine charts and more about developing reputable practices. See closely, act early, dose carefully, and speak plainly. Turn what you discover in a discomfort monitoring program right into muscle memory. With time, you will feel the shift. The patient who can not take a breath via broken ribs will certainly take a complete, stable breath while you change the cushion. The young adult with a dislocated shoulder will certainly nod when you tell them the following minute will really feel unusual, then relax as the joint slides home. The team will look to you when discomfort intimidates to thwart treatment, because you make it routine.
For nurses, that is the pledge of straightening with PUAEME008 offer discomfort management: less minutes of vulnerability, even more minutes of decisive relief, and a technique based in skill, compassion, and safety. Whether you pursue a formal discomfort management accreditation, a targeted pain management certificate course, or pile units within a bigger program, the genuine procedure rests at the bedside. Pain will certainly keep coming. With the best training, you will certainly fulfill it well.